Filter :

If you have PMOS (formerly known as PCOS), you have probably heard that managing your weight and metabolic health can be an important part of treatment. But that can be easier said than done. PMOS can involve insulin resistance, higher levels of androgens such as testosterone, and metabolic changes that may make weight management more challenging for some people.
That is one reason GLP-1 medicines have entered the PMOS conversation. These medicines are used for conditions such as obesity and type 2 diabetes, and research is exploring their potential role in women with PMOS who have metabolic concerns. But exactly how can GLP-1 medicines help in managing PMOS, and who might benefit from them? Keep reading to find out.
Table of Contents
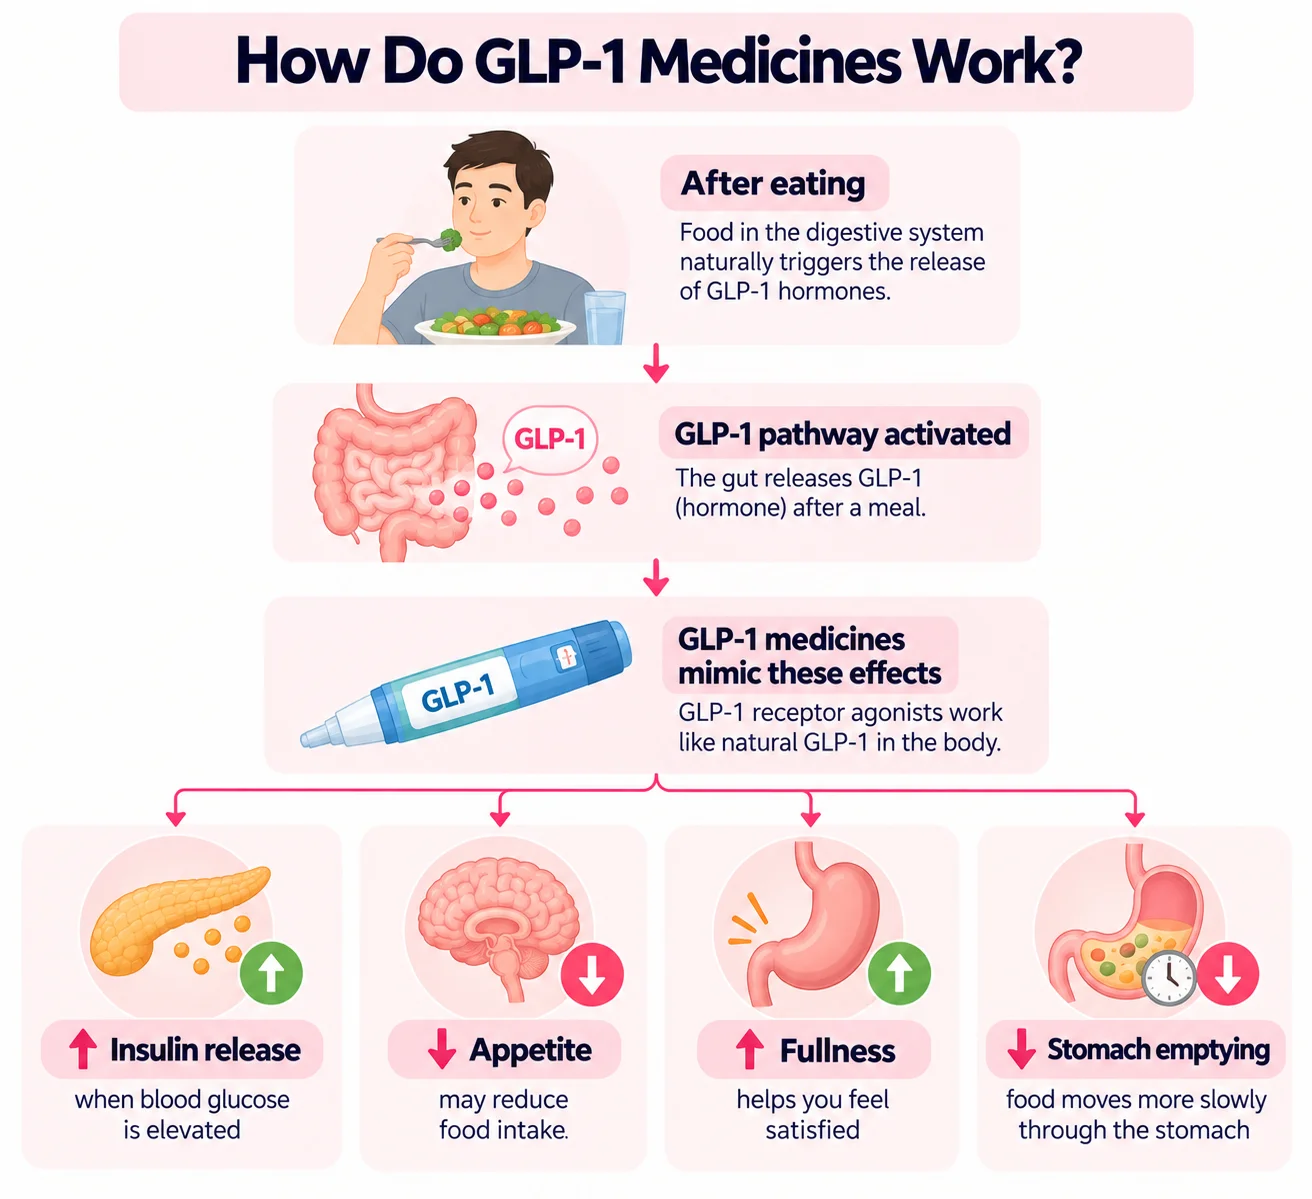
GLP-1 stands for glucagon-like peptide-1, a hormone naturally produced by the body after eating. It helps regulate your blood sugar and also influences appetite and digestion.
GLP-1 receptor agonists are medicines that mimic some of these effects. They can:
Semaglutide and liraglutide are GLP-1 receptor agonists. Tirzepatide works on GLP-1 as well as another hormone pathway called GIP.
PMOS (Polyendocrine Metabolic Ovarian Syndrome) can involve both reproductive and metabolic changes. Some people experience insulin resistance, which means the body’s cells do not respond to insulin as effectively as they should. The pancreas may compensate by producing more insulin.
This matters because metabolic changes can interact with the hormonal features of PMOS. At the same time, not everyone with PMOS has the same metabolic profile, so a GLP-1 medicine is not always appropriate just because someone has PMOS.
No. GLP-1 medicines do not treat PMOS as a whole. They may help with certain metabolic concerns associated with the condition, particularly higher weight and some measures of insulin resistance.
A PMOS diagnosis alone is not enough to decide whether you need a GLP-1 medicine.
A gynaecologist may consider factors such as:
For weight management, medicines are generally considered when excess weight is affecting health and when the person meets relevant prescribing criteria.
An important point that is sometimes missed is that healthy lifestyle changes can benefit PMOS even when they do not result in weight loss. The international PMOS guideline recognises that healthy lifestyle behaviours can provide health benefits even in the absence of weight loss.
That means treatment should focus on metabolic and reproductive health, not simply the number on the weighing scale.
Some studies have reported more regular menstrual cycles and improved natural pregnancy rates among women with PCOS taking GLP-1 receptor agonists. These effects may be indirect. By helping with weight management and some aspects of metabolic health, GLP-1 medicines may improve the hormonal and metabolic environment that influences ovulation in some women.
So, GLP-1 medicines should not be viewed as fertility medicines. Any improvement in ovulation or periods may be related partly to changes in weight and metabolic health, and more research is needed.
Most side effects of GLP-1 medicines are not permanent. They are more likely to occur when you first start treatment or when the dose is increased, and become milder as your body adjusts to the medicine.
Digestive symptoms are among the most common side effects. These can include:
This is why GLP-1 medicines are usually started at a lower dose and increased gradually. If side effects are severe, persistent or affecting your ability to eat or drink normally, speak with your doctor instead of changing or stopping the medicine yourself.
No. GLP-1 medicines and metformin work differently and are not interchangeable.
Metformin is a medicine that improves the body’s response to insulin and is commonly used in metabolic management of PMOS. GLP-1 medicines act through hormone pathways that influence appetite, blood sugar and digestion.
In some situations, a doctor may consider using different medicines together. The choice depends on the individual’s health.
GLP-1 medicines have opened another option for managing metabolic health in some people with PMOS, particularly when higher weight or related health problems are present. But they are not a treatment for every aspect of PMOS and should not be viewed as a quick fix for hormonal symptoms or fertility. The right treatment plan considers your symptoms, metabolic health, medications, weight and reproductive goals.
If you have PMOS and are wondering whether a GLP-1 medicine is a right option for you, a personalised discussion with a gynaecologist or metabolic specialist can help you understand where it fits into your overall care. The multidisciplinary healthcare team at the CK Birla Hospital can help you discuss your symptoms, metabolic concerns and treatment options in the context of your individual health goals. Simply book a consultation to get expert advice.

Anyone who has had a migraine knows it is not ‘just an ordinary headache.’ The throbbing pain can come with nausea, vomiting, and a sensitivity to light and sound that makes you want to withdraw from everything around you. This neurological condition has a tendency to recur, and an untreated attack can last from 4 to 72 hours.
The right approach to tackle this condition is to consult a migraine doctor, ideally a neurologist, early and get a treatment plan that suits you. At the same time, there are many popular natural remedies, shared online and among friends and family, that promise to ease the pain. The question is, do they actually work?
Let’s find out!
Table of Contents
Migraine is thought to result from a mix of genes and how your brain and nerves process signals. If you have migraine, your nervous system may be more sensitive to changes, and triggers like poor sleep, skipped meals or stress can set off an attack.
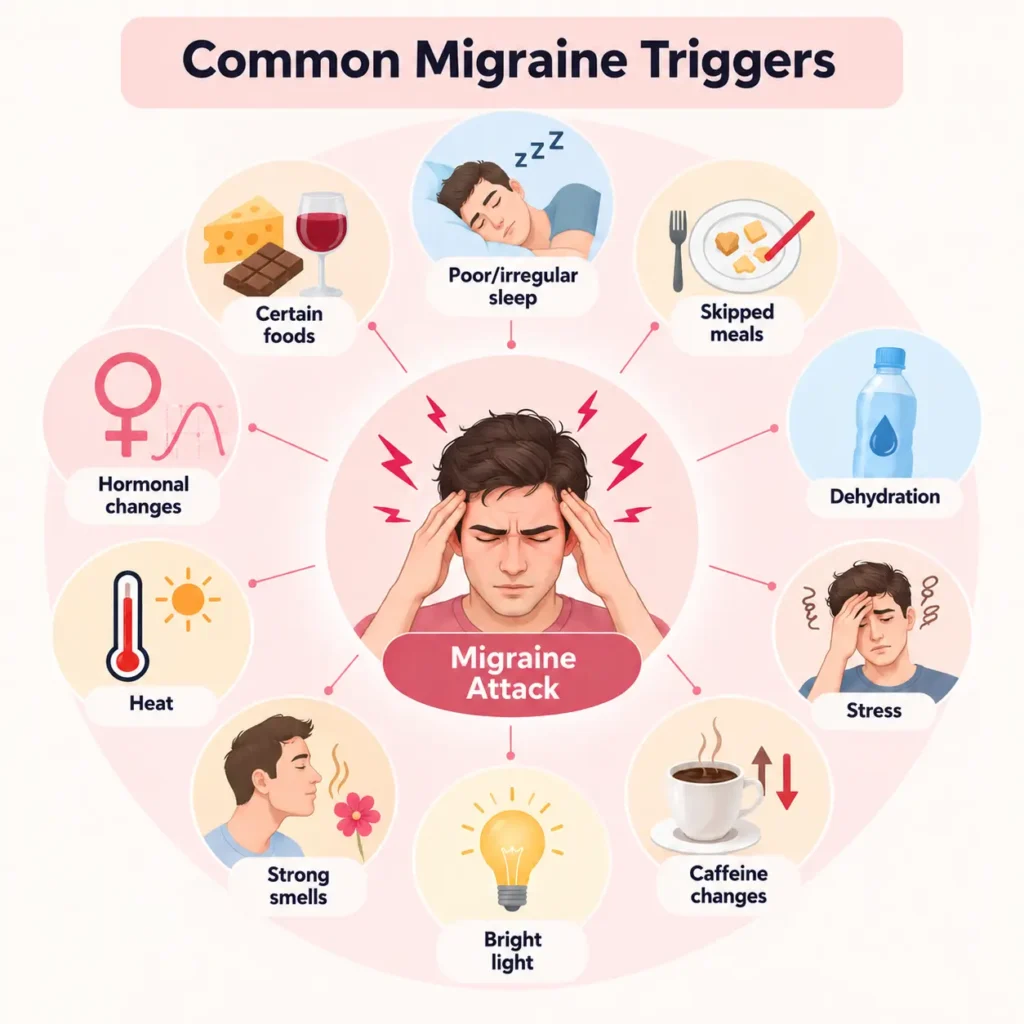
Some common triggers are:
One commonly overlooked point is that a trigger is not the underlying cause of migraine. It varies from person to person and can change over time. Keeping a migraine diary can help you find your own pattern, so you don’t end up avoiding a long list of foods or activities you didn’t need to.
The most popularly referred natural remedy online are essential oils. A pleasant smell may help some people relax, however essential oils are not a proven treatment for migraine.
In fact, strong smells can trigger or worsen an attack in some people, especially if they already have increased sensitivity to smell.
If you enjoy aromatherapy, use it only as a relaxation technique, and stop if the scent makes your symptoms worse. For now, the support is stronger for established measures like regular sleep, rest, and trigger management than for essential oils.
Some dietary supplements have been studied for migraine prevention, particularly magnesium, riboflavin (vitamin B2) and coenzyme Q10 (CoQ10).
But natural does not always mean safe. High doses of any supplement can cause side effects such as diarrhoea and stomach cramps and may interact with certain medicines.
If you are considering a supplement for migraine, speak to your doctor first. The right choice and dose depend on your overall health, medications and migraine pattern.
While there are no specific natural remedies, when you do feel a migraine beginning, small environmental changes may help you feel better. You can try:
Cold therapy for migraine may provide relief for some people, although others prefer warmth. Try what feels comfortable to you instead of forcing a particular method.
You can prepare a migraine kit before an attack happens. Keep water, your prescribed medication, a cold pack and an eye mask together so you do not have to search for them while dealing with severe symptoms.
There is no set migraine diet that prevents the headache for everyone. A food that triggers one person’s migraine may have no effect on another.
So, instead of eliminating multiple foods unnecessarily:
This approach can prevent another problem that is over-restricting your diet because you are afraid of triggering a migraine.
Your daily routine can play an important role in migraine management. You can try following the SEEDS approach recommended by the American Migraine Foundation:
Something many people don’t realise is that too much sleep or a sudden change in your usual sleep pattern can also be associated with migraine attacks. Consistency is generally more useful than simply trying to sleep as much as possible.
Regular, moderate exercise may help some people reduce migraine frequency and improve overall wellbeing. Walking, yoga and stretching are easy places to start. Go slowly, and build up over time.
During an active migraine attack, though, exercise may make symptoms worse. So, stop if any activity increases your pain, nausea or dizziness.
Yoga, deep breathing and other relaxation methods may help you manage stress, which is a common trigger, and they are low risk to try alongside your usual care. Physiotherapy can help when neck or muscle problems contribute to headaches, but it works best when it is guided by a professional and planned around your symptoms.
Home remedies may help manage migraine in some people, but recurrent migraines must get proper medical evaluation. A neurologist who specializes in migraine can work out whether your symptoms are really due to migraine and build a treatment plan based on how often and how severely you have attacks.
You should seek medical care if:
If you are experiencing recurring migraine attacks, don’t rely solely on home remedies. Getting the right diagnosis and treatment can help you manage it more effectively and reduce its impact on your everyday life.
Get Personalised Migraine Care at the CK Birla Hospital
If you are looking for a migraine treatment, you can book a consultation with us at the CK Birla Hospital for a detailed evaluation and a personalised treatment plan.

You may have heard of Botox for beauty treatments. But for migraines?
Yes, it is true! Botox is not limited to cosmetic use. It is widely used for medical purposes too. Many neurologists prescribe it in suitable cases to prevent chronic migraines, offering hope to people who live with severe, frequent headaches.
So, how does it work? Is it safe? And is it right for you? Keep reading to find out.
Table of Contents
Botox is a brand name for onabotulinumtoxinA, a purified form of botulinum toxin type A and it is available by prescription only. It temporarily calms down the activity of certain nerves and muscles.
Doctors have used this effect for many years to treat several medical conditions, and chronic migraine prevention is one of them.
When Botox is injected into specific areas around the head and neck, it can affect the release of certain chemical signals involved in pain transmission. In simple terms, Botox can help turn down some of the pain signalling associated with migraine. It also temporarily reduces activity in the muscles where it is injected.
The treatment is not simply about relaxing forehead muscles. Its benefit comes mainly from how it affects the sensory nerves that carry pain signals.
The aim is also not to eliminate every headache immediately. Instead, treatment seeks to reduce the overall burden of migraine over time.
Botox is primarily used for chronic migraine, not for people who experience an occasional migraine attack.
Whether it is appropriate depends on various factors, including how frequently you have headaches, how disabling they are, your previous treatments and your overall health.
NICE recommends botulinum toxin type A as an option for preventing chronic migraine in adults when at least three preventive medicines have not worked, have not been tolerated or are unsuitable, and medication overuse has been appropriately managed. Recommendations and access criteria can vary between healthcare systems.
This means Botox is not necessarily the first preventive treatment a person with migraine will be offered.
Your neurologist may discuss other preventive medicines or treatments first and then consider Botox if appropriate.
Migraine Botox is quite different from cosmetic Botox.
Treatment involves a series of small injections across specific areas of the head and neck.
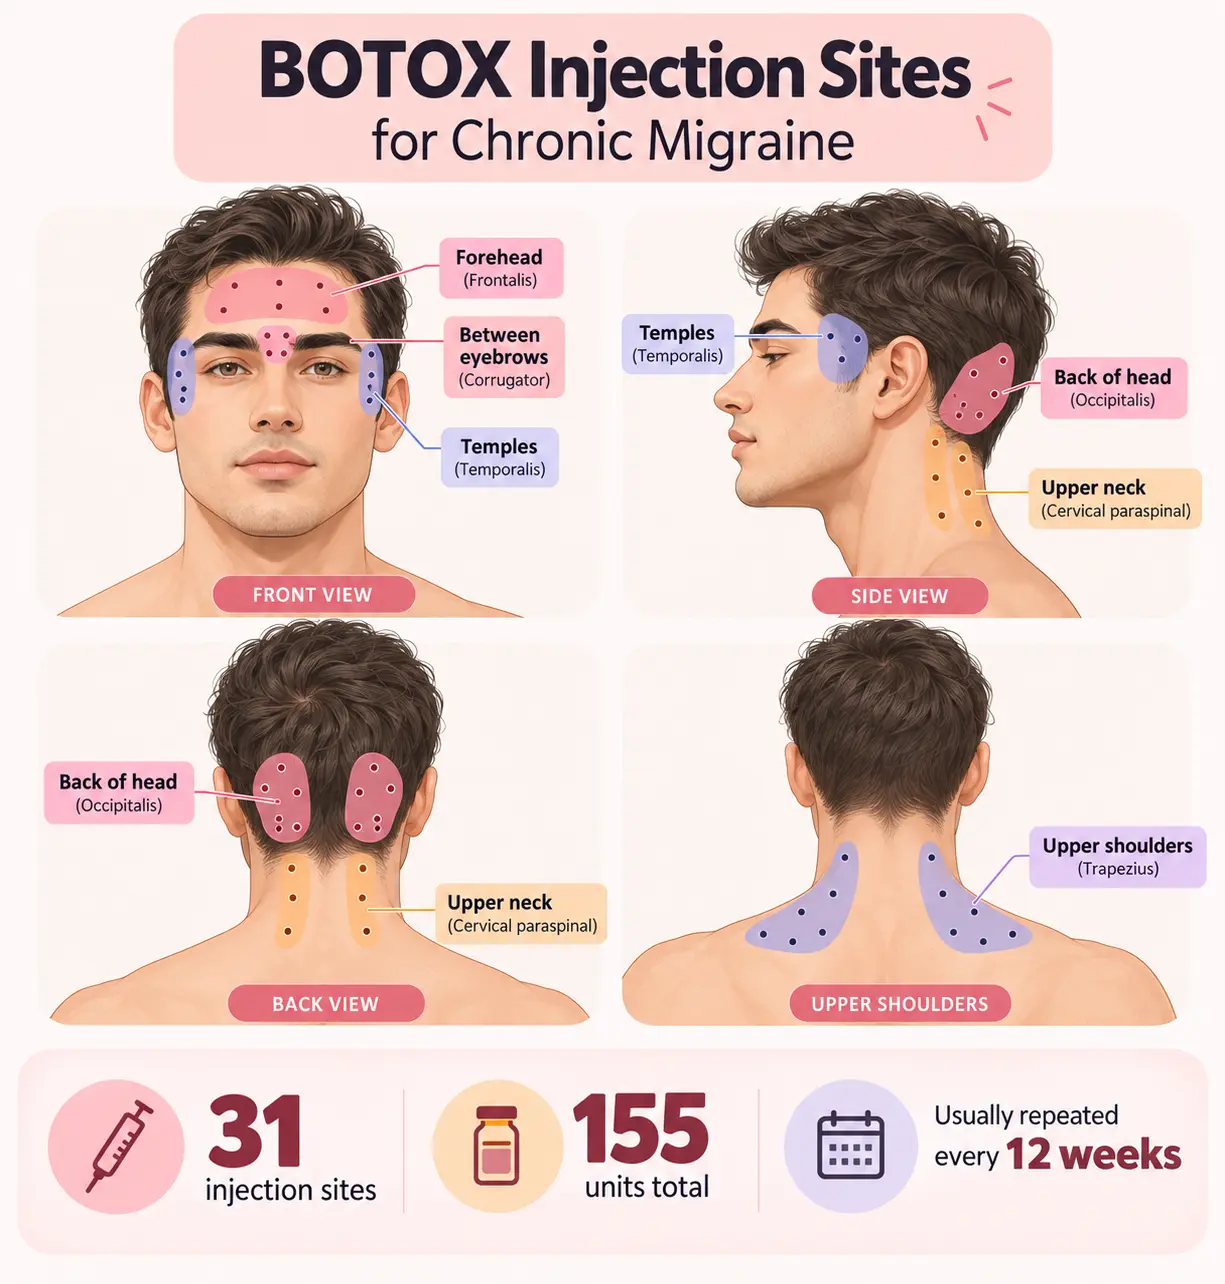
The FDA-recommended dose for chronic migraine is 155 units, as 0.1 mL (5 Units), divided across 31 small injection sites in seven areas of the head, neck and shoulders, including the forehead, temples, back of the head and neck.
Treatment is usually repeated every 12 weeks. That number can sound intimidating, but each injection contains a small amount of medicine and uses a fine needle. It is quick, and you can usually go home the same day. No hospital stay is needed.
Does Botox for migraine mean getting injections directly into the painful area?
Not necessarily. Your doctor follows a set pattern of injection sites around the head, neck and shoulders, instead of just aiming at wherever your head hurts during an attack. That’s because migraine is not a problem with one sore muscle. It is a neurological condition that involves pain signalling, and the treatment is designed with that in mind.
Botox is a preventive treatment, so it is not something you are given when a migraine starts. Instead, it is given on a regular schedule, usually about every 12 weeks. Some people notice a change after the first round, but one round is not usually enough to judge, so your doctor will usually look at how your headache days change over a few months.
Here, maintaining a headache diary that mentions your headache days, migraine days, severity, symptoms and any acute medicines, makes the review much easier, and helps your neurologist decide whether to continue, change or combine treatments.
Botox can reduce how often chronic migraine strikes. However, its effectiveness varies from person to person. Some studies show that, on average, people treated with onabotulinumtoxinA have fewer headache days each month.
Botox is generally well tolerated when appropriately administered, but side effects can occur.
Some people may experience:
The effects are usually temporary.
Another concern many patients have is whether migraine Botox will make their face look frozen. The treatment pattern for chronic migraine is designed for a medical purpose and differs from cosmetic Botox. Changes in facial movement can still occur in some people, which is why the procedure should be performed by a healthcare professional experienced in its use.
No. Botox is one of several preventive treatment options available for migraine.
Depending on your symptoms and medical history, your neurologist may consider oral preventive medicines, treatments for migraines called CGRP, neuromodulation devices or other approaches. The right treatment is therefore not simply the one that sounds most advanced or convenient. It is the one that fits your migraine pattern, other health needs, previous treatment response and preferences.
Yes. Botulinum toxin has uses beyond chronic migraine.
Neurologists may use it in selected patients with conditions involving excessive or involuntary muscle activity, including:
These uses are separate from migraine treatment, and the injection sites and treatment plans differ according to the condition.
If headaches are becoming more severe, frequent, interfering with your work or everyday activities, it may be time to discuss preventive treatment with a neurologist.
A specialist can evaluate your headache pattern, confirm whether you have chronic migraine, review previous treatments and discuss options such as botulinum toxin when appropriate.
So, if migraine is taking too much time away from your everyday life, consult the Neurology team at the CK Birla Hospital to understand your treatment options and find an approach suited to your symptoms.
Have you noticed a dark patch of skin on your neck, under your arms, or in the folds of your elbows and knees? One that does not go away no matter how much you wash or scrub? You may have assumed it is dirt, a tan line, or dry skin, but that’s usually not the case.
This is a skin condition called Acanthosis Nigricans, and it points to some health changes happening in your body, such as insulin resistance, hormonal changes, or PCOS. So before you start scrubbing hard to get rid of this patch, read this blog to know what causes it, what it may indicate, and how to treat it.
Table of Contents
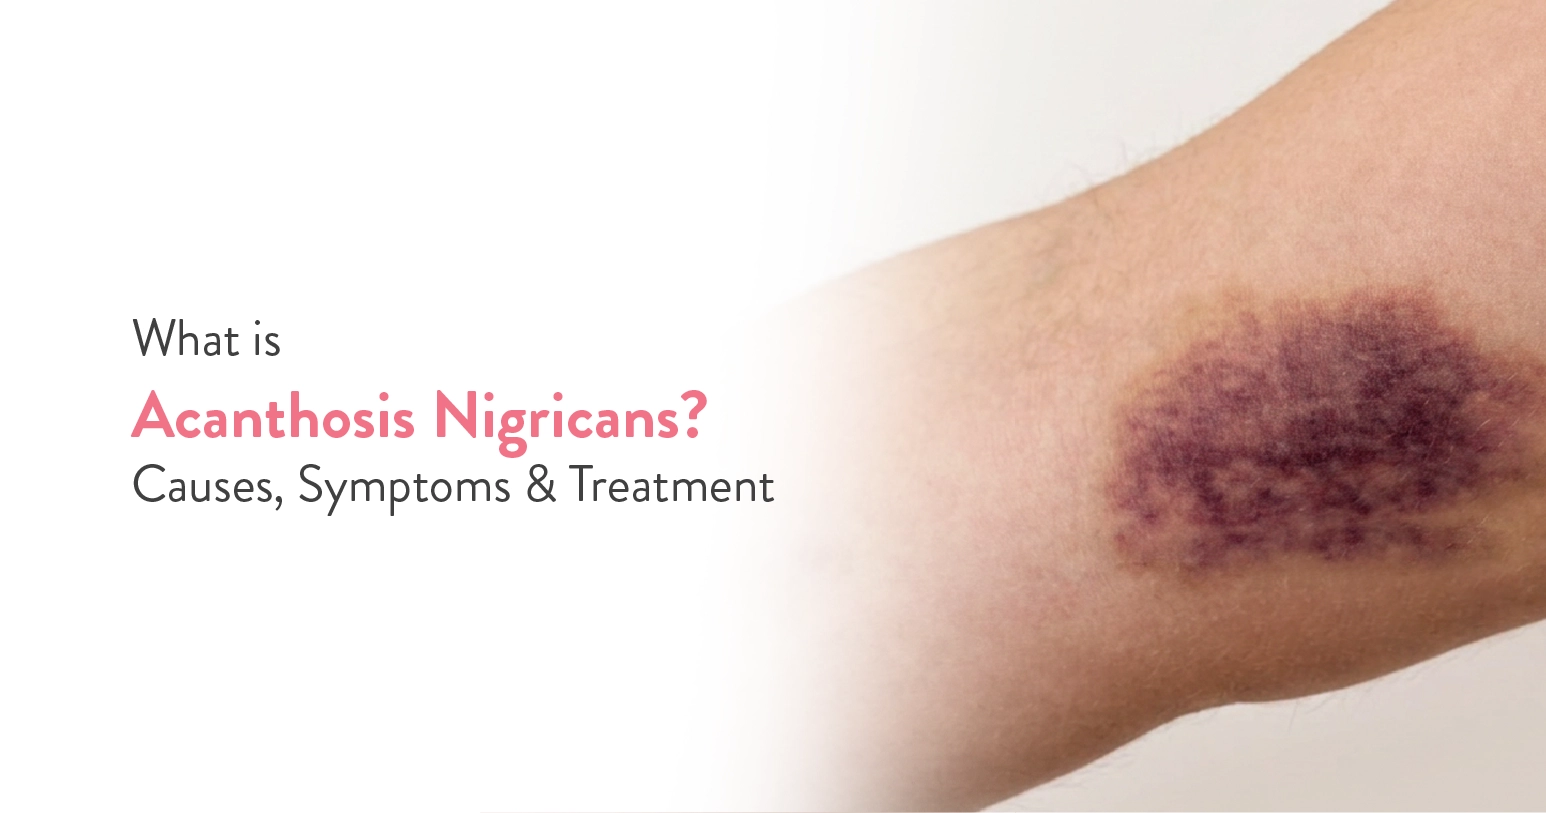
Acanthosis nigricans is a skin condition that causes areas of skin to become darker, thicker and velvety. It most commonly develops in skin folds and creases, especially the back of the neck, armpits and groin. It can also be seen on your elbows, knees, knuckles, under the breasts and other areas.
The condition is not contagious and cannot spread from one person to another. It is also not caused by dirt or lack of cleanliness. Scrubbing the affected skin harder will not remove it and may irritate the area.
One of the reasons this condition gets medical attention is its connection to insulin resistance.
Insulin is a hormone that helps the body use glucose, or sugar, from the blood. When the body’s cells do not respond to insulin effectively, the body may produce more insulin to compensate. Higher insulin levels can contribute to the skin changes seen in acanthosis nigricans.
But remember acanthosis nigricans does not always mean that you have diabetes. It can also be seen in people without diabetes or another underlying illness.
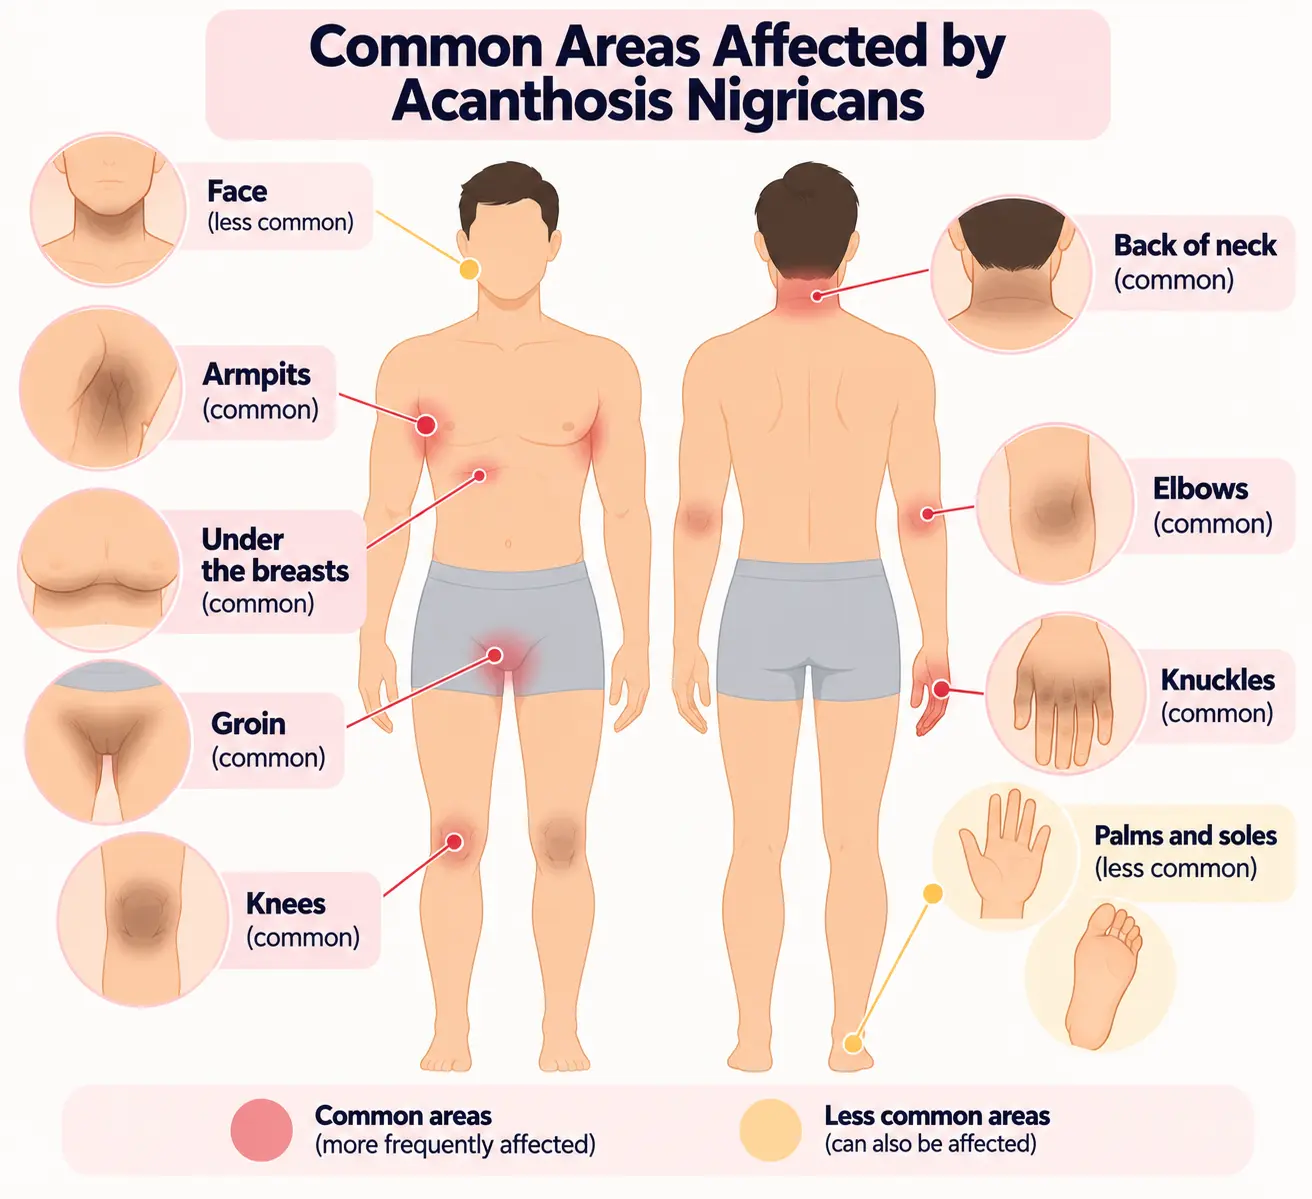
The skin changes are usually gradual and may develop over months or years.
Some common acanthosis nigricans symptoms are:
The back of the neck is a particularly common area. Some people first notice the condition when the skin looks darker in photographs or when a collar area becomes visibly different. It can also occur on your knuckles, elbows, knees, face, palms and soles.
Acanthosis nigricans can be due to several possible causes. The most common causes are linked to excess weight and insulin resistance, but these are not the only possibilities.
This is one of the biggest causes to watch out for. Insulin resistance can start well before your blood sugar levels are high enough to be called diabetes. That means Acanthosis Nigricans can show up even if you have not been diagnosed with prediabetes or insulin resistance yet. This is exactly why a new dark, velvety patch on your skin should not be brushed off as just a cosmetic issue.
Excess body weight is a common risk factor for acanthosis nigricans. When insulin resistance is also part of the problem, working on your overall metabolic health like managing weight and blood sugar can help improve the skin too.
Conditions that affect hormone levels can be linked with acanthosis nigricans. These include PMOS (Polyendocrine Metabolic Ovarian Syndrome) and certain thyroid or adrenal disorders.
Some medicines can result in these dark, velvety patches as a side effect. If you think a medicine you are taking might be causing your skin changes, don’t stop taking it on your own. Talk to your doctor first, they can figure out if switching to a different option makes sense for you.
Some people develop Acanthosis Nigricans simply because of their family history. In rare cases, it can also be linked to certain inherited conditions.
If there is a possibility of an underlying condition, your doctor may recommend tests based on your symptoms and medical history. These may include blood tests to check blood glucose and evaluate for conditions such as diabetes.
Your doctor may also ask about:
If you have noticed these dark patches, you can initially consult an internal medicine doctor. Based on your condition, they will refer you to the right specialist.
Over-the-counter creams and soaps are not a cure for acanthosis nigricans. The right treatment depends on what is causing it in the first place.
If insulin resistance, prediabetes, diabetes or another hormonal condition are the reason behind your skin changes, managing that condition is usually the priority.
If your condition is related to excess weight and insulin resistance, working on these areas can help. Gradual weight loss, regular physical activity, and better eating habits can improve how your body handles insulin and as that improves, your skin often starts to normal too.
If your skin changes are the side effects of certain medicine, your doctor may consider changing the medicine when appropriate.
There is no guaranteed home remedy that can remove acanthosis nigricans by itself.
If insulin resistance or excess weight is contributing to the condition, healthy lifestyle habits can be useful as part of medical care.
Note: These habits work alongside your medical treatment. They are meant to support it, not replace it.
Avoid aggressive home remedies
Lemon juice, baking soda, harsh scrubs and unprescribed bleaching products are not reliable treatments for this condition. They can irritate your skin and potentially make pigmentation more evident.
If you notice any new dark, thick, or velvety patches, particularly around the neck, armpits, or groin, you can initially consult an internal medicine doctor. Based on your condition, they may refer you to the right specialist if needed.
Seek medical evaluation promptly if the changes:
Don’t just treat the dark patch, treat the cause. Take this skin condition as a message from your body that something needs attention, and the right treatment starts with figuring out what that is. So the next time you notice a new dark, velvety patch, skip the scrubbing and the home remedies and go see a doctor instead. At the CK Birla Hospital, we have a multidisciplinary team of doctors who can help you get to the bottom of it. Book a consultation today to find the right answers for your condition.
Right now, as you read this, is your neck bent forward or your shoulders rounded? If your posture looks like this most of the day and your neck often feels stiff, tight, or strangely inflexible, you may be seeing the first signs of cervical pain.
Cervical pain has become one of the most common complaints of our time, yet most people ignore it until it starts affecting their sleep, work, and daily life. So before that stiffness turns into unbearable pain, read on to learn the symptoms, causes, diagnosis, and treatment of cervical pain.
Table of Contents
Cervical pain is basically pain, stiffness, or discomfort you feel in your neck, especially around the cervical spine. That’s the top part of your backbone, the part that holds up your head and lets you turn, nod, and tilt it.
Sometimes the pain stays in your neck. Other times it travels to your shoulders, upper back, arms, or even your hands, depending on what is causing it. The common reasons behind it are muscle strain, poor posture, age-related changes in the spine, an injury, or an irritated nerve.
Cervical pain can build up from everyday habits, changes in the spine, or a sudden injury. Here are the most common causes:
How do you know if your neck problem is more than a simple stiff neck? Watch for these signs:
If a nerve is irritated or compressed, the symptoms may extend beyond the neck. This is called cervical radiculopathy (pinched nerve), meaning a nerve root in the neck is affected. It can cause pain, tingling, numbness or weakness along the affected arm.
Note: See a pain management specialist right away if you have severe pain after a fall or accident, neck stiffness with fever, weakness that keeps getting worse, trouble walking or balancing, or loss of bladder or bowel control.
There are two main ways to group cervical pain: by how long it lasts and by what causes it.
How long does Cervical Pain last?
What’s causing Cervical Pain?
Different types of pain have different causes, so knowing yours helps you get the right treatment.
A pain management specialist will usually begin by asking about:
A physical examination may be done to evaluate your neck movement, muscle strength, sensation and reflexes. Imaging tests such as an X-ray, CT scan or MRI may be recommended if needed.
The right treatment depends on what is causing your pain, how bad it is, and what symptoms you have.
Treatment may include:
For mild neck pain without concerning symptoms, simple measures may provide relief. You can try:
Do not rely on home treatment if the pain is persistent, worsening or associated with numbness, weakness or pain travelling into the arm.
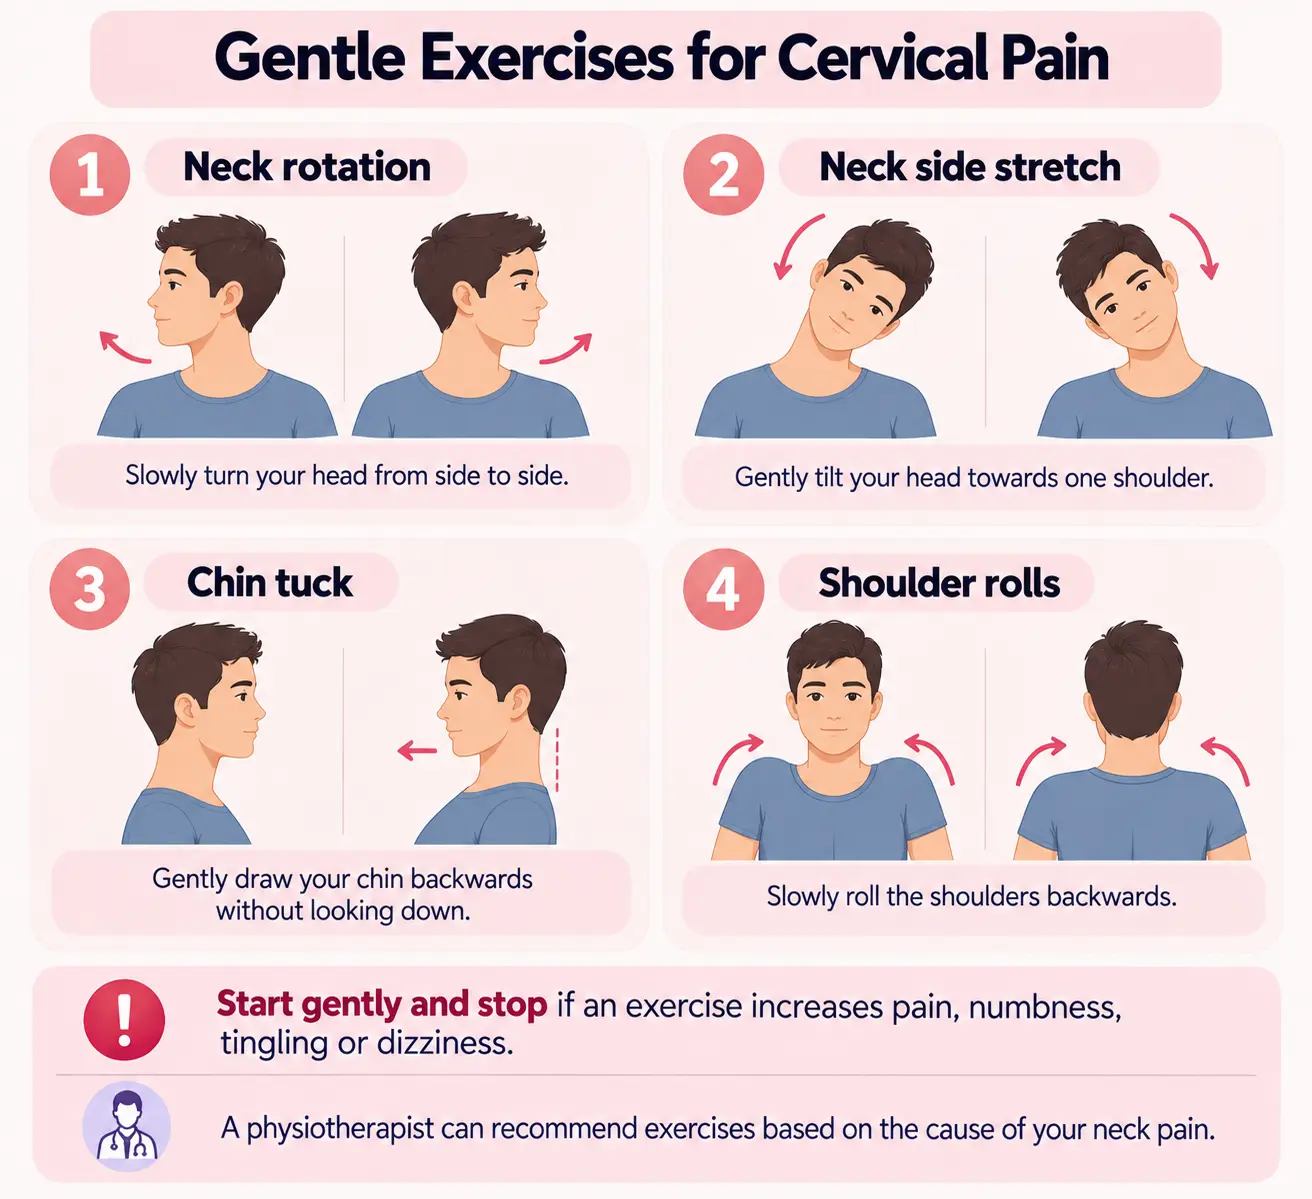
Consider medical evaluation if your cervical pain:
You should get medical help right away if you have severe neck pain after a major injury, weakness that is new or getting worse, trouble walking or keeping your balance, or new bladder or bowel problems. These can mean the nerves or spinal cord are affected and need to be checked quickly.
Get Expert Care at The CK Birla Hospital
You don’t have to live with persistent neck pain. Our team of pain management specialists, neurologists, and spine care experts at the CK Birla Hospital will help you understand the cause behind your pain and guide you towards the right treatment and rehabilitation. Simply call us to book a consultation.

You sip water, clear your throat, hold your breath, and try everything else to hold it in, but a dry cough always finds a way to burst out in the quietest room. What makes it worse is that tickly, scratchy irritation in your throat that comes with it.
If this is happening to you, keep reading! By the end of this blog, you will know why the dry cough is happening, how to treat it, and what to skip to prevent it.
Table of Contents
A dry cough is a cough that produces little or no mucus or phlegm. It may feel like a tickle or irritation in the throat and can sometimes occur in repeated bursts. It is generally provoked by irritation or inflammation, not an infection that produces mucus.
Most dry coughs don’t last long. Colds, flu, dry air, dust, and allergies are common causes, and they normally ease within a couple of weeks. In many cases, it is just your throat taking its time to heal.
For adults, coughs are generally classified by how long they last:
An acute cough usually improves within 3 weeks, particularly when it is caused by a viral respiratory infection. A cough that continues beyond 3 weeks, keeps returning or is getting worse and is accompanied with other symptoms like fever then it needs an expert evaluation as it may indicate the onesie of pulmonary TB.
Besides coughing without producing mucus, you may experience:
The pattern of your cough can help find the cause behind it. For example, if it gets worse at night after you lie down, the cause may be different from a cough that starts when you are around dust, smoke, or cold air.
Some common causes are:
If the cough is very mild and there are no serious signs, a little self-care may help you.
Note: These measures are for symptom relief, not a cure for every cause of dry cough.
A dry cough can feel particularly troublesome at night.
If it flares up when you lie down, a blocked nose (nasal congestion), postnasal drip, or acid reflux could be the reason.
Keeping your bedroom free from smoke and other irritants may help.
Staying hydrated during the day can also reduce throat dryness.
If your cough repeatedly wakes you up, lasts for weeks or is accompanied by other symptoms, don’t keep trying new remedies indefinitely. An internal medicine doctor can help identify the reason behind the nighttime cough.
There is no universal way to cure dry cough quickly because treatment depends on its cause.
For example, a cough caused by an infection may improve as the infection settles, whereas asthma, reflux or a medicine-related cough requires a different approach. Over-the-counter cough syrups or tablets may give short-term relief, but they don’t deal with the root cause, which means the cough can come back later.
This is why a persistent cough should not be treated solely based on random recommendations from someone you know, a social-media hack or a leftover medicine at home.
Never start antibiotics on your own just because a cough has lasted several days. Most uncomplicated cases of acute bronchitis are caused by viruses, and antibiotics do not help. Unnecessary antibiotic use can also cause side effects and contribute to antibiotic resistance.
Similarly, do not take someone else’s prescription medicine or stop your own medication without medical advice.
See a healthcare professional if your cough:
If you have serious difficulty breathing, severe chest pain, or symptoms that worsen quickly, get urgent medical help. For a persistent cough, you can see a general physician or an internal medicine doctor.
A doctor will usually ask about your health history, medicines, smoking, and pollution exposure, and may follow up with a physical exam. In some cases, they may also ask for a chest X-ray or a breathing test called spirometry.
Don’t let a persistent cough affect your daily life. If your dry cough is persistent or recurring, our Internal Medicine specialists at the CK Birla Hospital can help. You can simply reach out to us or call to book a consultation.

Does your chest look fuller than you’d like, sometimes making you feel self-conscious?
For many men, the chest is one of the areas where excess body fat becomes very noticeable. If you are looking for ways to reduce it, keep reading to learn what causes chest fat, which diet and exercise changes work, and the daily habits that can help.
Table of Contents
Chest fat is usually linked to an increase in overall body fat. When the body stores excess energy as fat, some of it may accumulate around the chest.
Genetics also influence where a person tends to store fat, so two men with similar body weights may notice fat in different areas.
Some common causes and contributing factors are:
Being overweight can also make your chest look enlarged because fatty tissue can develop around the breast area. In some men, this is called pseudogynecomastia, which means increased fat tissue without enlargement of the breast gland.
There is another possibility: gynecomastia. This happens when breast gland tissue grows, often because of changes in the balance between testosterone and estrogen. Certain medicines, anabolic steroids, puberty, ageing and some health conditions affecting the thyroid, liver, kidneys or testes can be associated with gynecomastia.
This is one of the most common questions men have when they notice chest enlargement.
| Chest fat (pseudogynecomastia) | Gynecomastia |
| Mainly excess fatty tissue | Enlargement of breast gland tissue |
| Associated with overall weight gain | Linked to hormonal changes or certain medicines |
| May decrease as overall body fat decreases | May not disappear simply through exercise |
| Usually feels soft | May feel like a firm, rubbery area beneath the nipple |
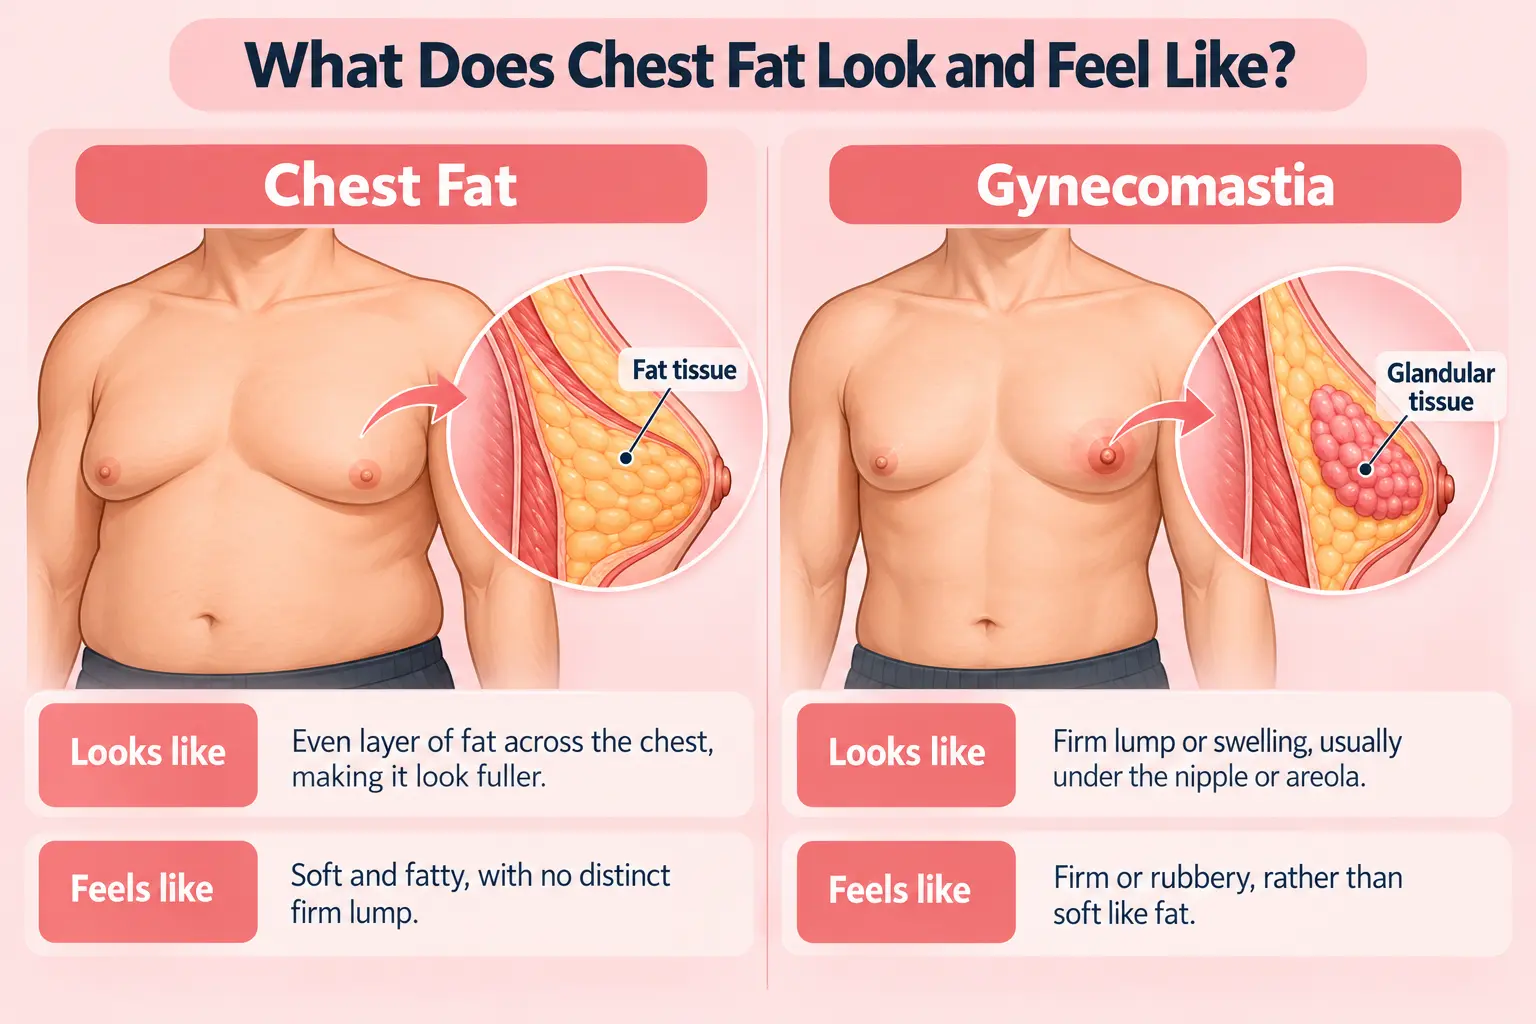
Chest fat and gynecomastia can also occur together. If you are unsure what is causing your chest enlargement, a healthcare professional, ideally an Aesthetic and Plastic Surgeon, can examine the area and, when needed, recommend blood tests or imaging tests to identify the cause.
If excess body fat is the reason behind your enlarged chest, the goal is overall fat loss, instead of trying to burn fat from the chest area alone.
You cannot choose exactly where your body loses fat first. Instead, focus on a combination of regular physical activity, strength training and a balanced eating pattern.
Chest exercises are useful, but there is a common misconception that they directly burn chest fat. Exercises such as push-ups and bench presses strengthen the chest muscles underneath the fat; they do not selectively remove fat from that area.
A practical exercise routine can include:
Remember: If chest enlargement is due to gynecomastia, exercise can improve overall chest appearance but cannot remove the underlying glandular tissue.
There is no specific food that burns chest fat. Instead, your diet should support gradual, sustainable reduction in overall body fat.
Build most meals around:
At the same time, try to reduce frequent consumption of sugary drinks, highly processed snacks, deep fried foods and foods that are very high in calories but low in nutritional value.
A very restrictive diet is also not necessarily a better diet. Rapid weight loss attempts can be difficult to sustain and may also result in loss of lean tissue. That’s why a moderate, consistent approach is generally more practical for long-term weight management.
Lifestyle Changes That Can Help
Small, consistent changes outside your workout can also help in healthy fat loss. Aim for:
You do not need to make drastic changes overnight; building habits you can maintain is more likely to support lasting results.
It is not necessary. However, you do need to be disciplined and exercise regularly. Since chest fat is part of overall body fat, regular physical activity that helps you manage your weight can be effective.
Brisk walking, cycling, swimming, climbing stairs and bodyweight exercises such as push-ups and squats are good options. What matters most is consistency. If you are mostly sedentary, start with a daily walk and gradually increase your activity.
If you are new to exercise, consider professional guidance to learn proper form and choose exercises suited to your fitness level.
It is worth getting a medical check-up if you notice any of the following:
These signs can point to something other than excess body fat, so it is best not to assume and wait.
For any questions about your body fat or other health concerns, our multidisciplinary healthcare team at the CK Birla Hospital is always here to help. You can start with our internal medicine specialists, who can refer you to an aesthetic or plastic surgeon for specialised treatment when needed. Simply call us to book a consultation.

With PCOS recently renamed PMOS, the spotlight has finally moved beyond reproductive symptoms and onto the metabolic factors driving this condition. Insulin resistance, in particular, is now being looked at more seriously.
In this blog, we will discuss how insulin resistance and PMOS are connected, and why it matters for how you manage it. Keep reading to find out!
Table of Contents
| PMOS (Polyendocrine Metabolic Ovarian Syndrome) | Insulin resistance |
|---|---|
| It is a chronic hormonal condition and metabolic disorder that can affect your menstrual cycle, ovulation, fertility and overall health. | It is a state in which the body’s cells respond less effectively to insulin. |
| This condition can cause irregular periods, problems with ovulation, acne and excess hair growth. | The pancreas may produce more insulin to keep blood glucose within range. |
| Symptoms and severity vary from person to person | Can occur before prediabetes or type 2 diabetes |
Insulin is a hormone that helps glucose move from the bloodstream into cells, where it can be used for energy. When the body becomes less responsive to insulin, the pancreas may produce more insulin to compensate. This is called insulin resistance.
A 2026 international consensus published in The Lancet introduced a new name for what was previously called PCOS: Polyendocrine Metabolic Ovarian Syndrome (PMOS).
The term PCOS placed a strong focus on the ovarian cysts only. However, decades of research have shown that the condition can affect reproductive, hormonal and metabolic health, not just the ovaries. Following a global consensus process, the condition was renamed Polyendocrine Metabolic Ovarian Syndrome (PMOS).
This name change also helps bring metabolic health into the conversation alongside menstrual and reproductive health.
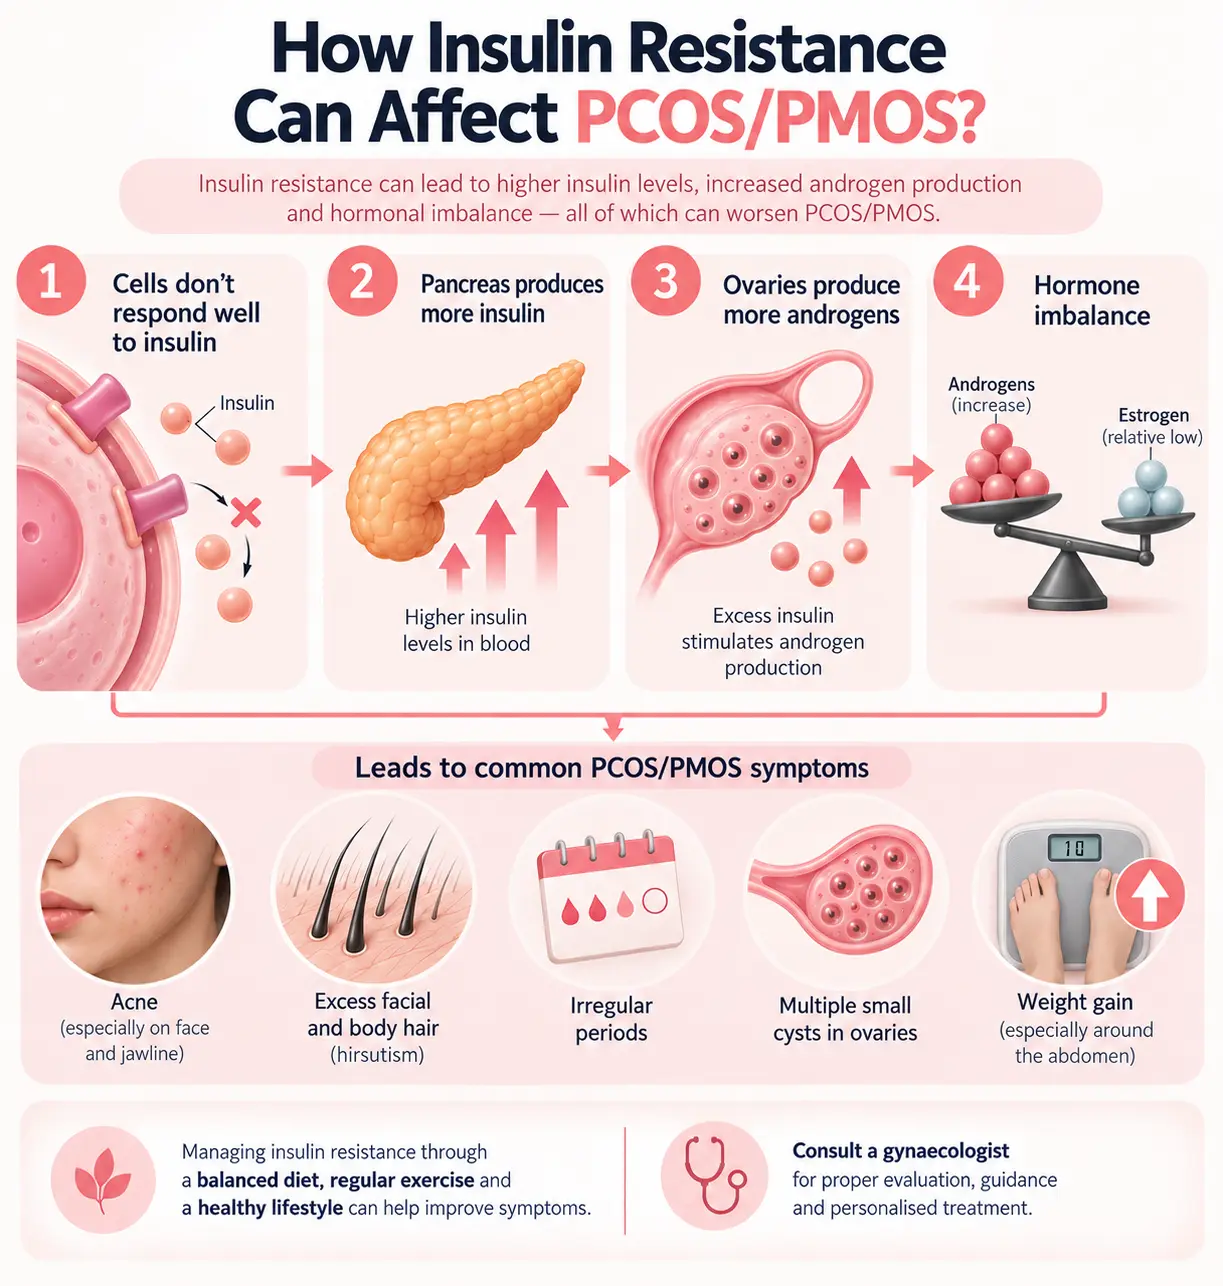
Insulin resistance can lead to higher levels of insulin in the blood, meaning your body pumps out more of it and that extra insulin signals your ovaries to produce more androgens (like testosterone) than usual. This can cause acne, excess hair growth, hair thinning, and irregular or irregular periods.
Higher androgens also affect ovulation, which is a big reason fertility issues are common with PMOS. The resulting hormonal imbalance may lead to weight gain, which can worsen insulin resistance further, creating a cycle that keeps reinforcing itself.
If it is not managed timely, it can raise the risk of type 2 diabetes and contributes to fatigue, sugar cravings, and stubborn weight.
In short, insulin resistance is not just about your blood sugar level, but it is also a major driver behind the hormone imbalance that shows up as PMOS symptoms.
A simplified way to understand the relationship is:
Insulin resistance → Higher insulin levels → Changes in ovarian hormone activity → Ovulation may become irregular →Periods may become irregular
But remember that PMOS is not simply an insulin-resistance disorder. Your genetics, hormones, body composition and other metabolic factors also influence the condition. That means two people can have the same diagnosis but very different symptoms and health concerns.
Weight and insulin resistance can influence each other, but the relationship is more complex than insulin resistance simply causing weight gain.
Some people with PMOS find weight management difficult. Excess body fat can also worsen insulin resistance. At the same time, hormonal and metabolic changes may make weight management more challenging for some people with PMOS.
This is why metabolic health cannot be judged by weight alone.
A recent 2026 review of PMOS highlights earlier research showing insulin resistance in 75% of lean women with PCOS and 95% of women with overweight and PCOS. This is an important finding because it shows that insulin resistance can be seen even when a person is not overweight.
You can have PMOS and metabolic risk at different body sizes. International guidelines recommend checking glucose regulation in people with PMOS/PCOS regardless of BMI.
Yes. Insulin resistance can develop before blood glucose reaches the range used to diagnose prediabetes or diabetes. The body may initially compensate by producing more insulin, allowing blood glucose to remain within the normal range.
Over time, some people may develop prediabetes, when blood glucose is higher than normal but not yet in the diabetes range. Others may go on to develop type 2 diabetes.
This is particularly relevant in PMOS because the condition is associated with an increased risk of abnormal glucose regulation.
| Test | Normal | Prediabetes | Diabetes |
| Fasting blood glucose | Below 100 mg/dL | 100–125 mg/dL | 126 mg/dL or higher |
| HbA1c | Below 5.7% | 5.7–6.4% | 6.5% or higher |
| 2-hour glucose during an OGTT | Below 140 mg/dL | 140–199 mg/dL | 200 mg/dL or higher |
Since you can’t always spot insulin resistance from symptoms alone, doctors use a few standard tests to check for it:
If you have PMOS, don’t skip checking your insulin and glucose levels, even if your weight or symptoms don’t seem to point to it. Speak with a gynaecologist to get expert advice based on your overall health. They can evaluate your hormonal and reproductive health, and guide you on what tests you need and what lifestyle changes might help.
At the CK Birla Hospital, you can consult with some of the most experienced gynaecologists, who can give you the best advice for your individual health. Simply book a consultation to get answers specific to you.

भारत में प्रेगनेंसी की शुरुआत डॉक्टर के पर्चे से कम और दादी-नानी के नुस्खों से ज्यादा होती है। हर कोई आपको अपनी डाइट बदलने की सलाह देता है, लेकिन क्या “ज्यादा घी खाने” या “दो लोगों का खाना खाने” से बच्चा सच में स्वस्थ होता है?
जवाब है – नहीं। प्रेगनेंसी में आपके शरीर को एक्स्ट्रा कैलोरीज से ज़्यादा, सही विटामिन्स और मिनरल्स वाले भारतीय डाइट प्लान (Indian Pregnancy Diet Plan) की जरूरत होती है। सही पोषण न केवल बच्चे के शारीरिक और मानसिक विकास के लिए जरूरी है, बल्कि यह आपको थकान, कमजोरी और डिलीवरी की जटिलताओं से भी बचाता है। NFHS-5 के आंकड़े बताते हैं कि आज भी भारत में लगभग 52% गर्भवती महिलाएं एनीमिया (खून की कमी) का सामना कर रही हैं, जिसका मुख्य कारण गलत खान पान है।
आधी-अधूरी जानकारी आपकी और बच्चे की सेहत पर भारी पड़ सकती है। सही और वैज्ञानिक सलाह के लिए आज ही सीके बिरला अस्पताल के डायटीशियन और स्त्री रोग विशेषज्ञों (Obs and Gynae Specialist) से मिलें, और अपने लिए एक सुरक्षित, पर्सनलाइज्ड डाइट प्लान तैयार करवाएं।
Table of Contents
प्रेगनेंसी में आपके खान-पान का एक विशेष महत्व होता है। कुछ ऐसे खाद्य पदार्थ होते हैं, जिनका सेवन मां और बच्चे के लिए जरूरी होता है। चलिए समझते हैं कि गर्भावस्था में आवश्यक पोषक तत्व और उनके भारतीय खाद्य स्रोत –
गर्भावस्था की हर तिमाही में खानपान का महत्व अलग-अलग होता है। कुछ खाद्य पदार्थों को तीसरी तिमाही में खाने से लाभ मिलता है, तो कुछ के पहली तिमाही में सेवन से बच्चे को पूरा पोषण मिल सकता है।
गर्भावस्था की पहली तिमाही में क्या खाएं? इस दौरान अतिरिक्त कैलोरी की जरूरत लगभग नहीं होती। असली चुनौती मतली और उल्टी है, इसलिए लक्ष्य यह है कि जो पेट में टिके, वही खाएं।
अब भूख लौटती है और बच्चा तेजी से बढ़ता है। ICMR-NIN और ACOG जैसी संस्थाओं के अनुसार इस चरण में रोज लगभग 340 से 350 कैलोरी अतिरिक्त चाहिए। यह एक कटोरी दलिया और एक गिलास दूध जितना है।
बच्चे का वजन सबसे ज्यादा इसी दौरान बढ़ता है। जरूरत लगभग 450 अतिरिक्त कैलोरी की होती है, लेकिन बढ़ता गर्भाशय पेट पर दबाव डालता है, इसलिए भोजन छोटे और बार-बार लें।
कुछ लोग भारतीय खाद्य पदार्थों को अक्सर नजरअंदाज कर देते हैं, लेकिन ये भी प्रोटीन और फाइबर के अच्छे स्रोत हैं।
जेस्टेशनल डायबिटीज डाइट: मैदा, मिठाई और मीठे जूस कम करें। ब्राउन राइस, ओट्स, दालें और हरी सब्जियां लें। भोजन बार-बार और छोटे हिस्सों में खाएं, और खाने के बाद 10 से 15 मिनट टहलें।
कई महिलाएं पूछती है कि प्रेगनेंसी में मछली खा सकती हूं? हां, रोहू, कतला जैसी कम पारे वाली मछली अच्छी तरह पकाकर हफ्ते में 2 बार तक ठीक है। शार्क, स्वोर्डफिश और किंग मैकेरल से बचें।
गर्भावस्था में क्या नहीं खाना चाहिए की सूची छोटी लेकिन जरूरी है –
कैफीन रोज 200 mg से कम रखें। यानी दिन में 1 से 2 कप चाय या 1 कप कॉफी तक।
प्रेग्नेंट महिलाओं के लिए ये एक आदर्श टाइमटेबल है, जिसमें आप कुछ फेरबदल करके फॉलो कर सकते हैं –
नोट: यह एक बेसिक रूटीन है, लेकिन हर किसी का शरीर अलग होता है, इसलिए अपनी डॉक्टर (गायनेकोलॉजिस्ट) की सलाह के हिसाब से इसमें बदलाव ज़रूर करें।
गर्भावस्था में “दो लोगों का खाना” खाने के बजाय सही पोषण पर ध्यान देना जरूरी है। तिमाही के अनुसार फोलिक एसिड, आयरन, कैल्शियम और प्रोटीन युक्त भारतीय आहार माँ और बच्चे दोनों को स्वस्थ रखता है। सही खानपान थकान और एनीमिया जैसी समस्याओं से बचाता है, जबकि अत्यधिक तला-मसालेदार और कच्चा भोजन नुकसान पहुंचा सकता है। अपनी और बच्चे की सुरक्षा के लिए कोई भी डाइट प्लान शुरू करने से पहले अपने डॉक्टर से परामर्श ज़रूर लें।

